
Facet joint pain is a common cause of neck and low back pain, particularly in adults with age-related degenerative changes of the spine. Facet joints are small joints located at the back of the spine that help guide and stabilize spinal movement. When these joints become inflamed or arthritic, they can generate localized pain and stiffness.
At our Miami clinic, we provide a comprehensive, non-surgical approach to facet joint pain treatment focused on accurate diagnosis, symptom relief, restoring mobility, and avoiding unnecessary surgery whenever possible.
Facet joints connect the vertebrae of the spine and allow for controlled motion such as bending and twisting. Each spinal segment contains a pair of facet joints, one on each side.
Facet joint pain typically results from:
Facet joint pain most commonly affects the:
Symptoms may vary depending on the location of the affected joints. Common symptoms include:
Unlike nerve-related pain, facet joint pain is usually more mechanical and position-dependent.
Facet joint pain may develop due to:
Facet joint degeneration often occurs alongside other spinal conditions, such as disc degeneration or spinal stenosis.
Accurate diagnosis requires careful clinical evaluation, as facet joint pain can mimic other causes of spinal pain. Evaluation typically includes:
Detailed medical history and symptom assessment
Physical examination focusing on pain patterns and movement
Assessment of posture, gait, and spinal mechanics
Review of prior imaging
MRI or X-rays when clinically indicated
Imaging findings are interpreted in conjunction with symptoms, as facet joint arthritis on imaging does not always cause pain.
Most patients with facet joint pain improve with conservative care.
Physical therapy is often foundational and may focus on:
Remaining active within pain limits is encouraged.
Medications are used strategically and at the lowest effective dose.
In select cases, image-guided procedures may be considered to help confirm the diagnosis and reduce pain:
These procedures are typically performed using fluoroscopic or ultrasound guidance to improve accuracy and safety.
For patients who respond well to diagnostic medial branch nerve blocks, radiofrequency ablation (RFA) may be considered. RFA uses targeted heat to interrupt pain signals from the medial branch nerves supplying the facet joints.
This procedure is not appropriate for all patients and is considered only after careful evaluation and diagnostic confirmation.
Facet joint pain is one of the conditions with the clearest and most evidence-based non-surgical treatment pathway available. Understanding this pathway helps set appropriate expectations and ensures patients receive the right treatment at the right time:
Not all axial back or neck pain is facet-mediated. The facet joint must be identified as the primary pain generator before any injection-based treatment is directed to it. Clinical features suggesting facet pain include axial pain without radiating limb symptoms, pain worsening with extension and rotation, and imaging showing facet arthropathy — though imaging alone cannot confirm the diagnosis.
A diagnostic injection — either directly into the facet joint or along the medial branch nerves supplying it — confirms the facet as the pain source. Significant pain relief following the injection supports the diagnosis and guides further treatment. These procedures are performed under fluoroscopic guidance with contrast confirmation.
For patients with confirmed facet-mediated pain following two positive diagnostic blocks, radiofrequency ablation disrupts the medial branch nerves transmitting pain from the facet joint — providing longer-lasting relief typically lasting 6 to 12 months or more. RFA does not damage the facet joint itself, only the small pain-conducting nerves.
For patients who want to address the underlying joint pathology rather than just the pain signal — or who are seeking an alternative to repeated RFA cycles — intraarticular BMAC stem cell therapy targets the facet joint itself. Emerging research suggests BMAC may modify the degenerative environment within the facet joint and reduce the frequency of symptom recurrence. See: Stem Cells for Lumbar Facet Pain — Evidence Review

Regenerative medicine for facet joint pain represents an emerging but promising approach that targets the arthritic joint itself rather than the nerves transmitting its pain signals. This is a fundamentally different biological strategy from RFA — one that may reduce the need for repeat nerve ablation by addressing the underlying facet arthropathy.
Intraarticular PRP delivers concentrated growth factors into the facet joint under fluoroscopic guidance, targeting the synovial inflammation and cartilage degeneration within the joint itself. PRP is most appropriate for patients with early to moderate facet arthropathy who have had good but temporary responses to facet injections.
For patients with more advanced facet arthropathy, BMAC delivers mesenchymal stem cells and growth factors directly into the facet joint under fluoroscopic guidance. A Phase I clinical trial evaluating stem cell therapy for lumbar facet joint pain demonstrated meaningful improvements in pain and function at 2-year follow-up, with some patients showing evidence of reduced facet degeneration on MRI — supporting the biological rationale for intraarticular stem cell delivery to the facet joint.
Dr. Bonner has published a clinical review of the evidence for stem cell therapy for facet pain: Stem Cells for Lumbar Facet Pain: Safety and Early Evidence
As a credentialed Regenexx network provider, Dr. Bonner performs all facet regenerative procedures under fluoroscopic guidance — the same image guidance standard used for all diagnostic and therapeutic facet procedures at our clinic.
| Treatment Type | Main Purpose | Expected Duration of Relief | Invasiveness |
|---|---|---|---|
| Physical Therapy | Improve mobility, posture, and strength | Long-term with compliance | Non-invasive |
| Medications | Reduce pain or inflammation | Short-term | Non-invasive |
| Steroid Injections | Reduce inflammation | Weeks to months | Minimally invasive |
| Regenerative Medicine (e.g., PRP) | Support tissue healing | Long-term | Minimally invasive |
| Surgery | Correct structural issues | Permanent | Highly Invasive |
Most patients benefit from a layered approach that incorporates rehabilitation, activity modification, and targeted interventions.
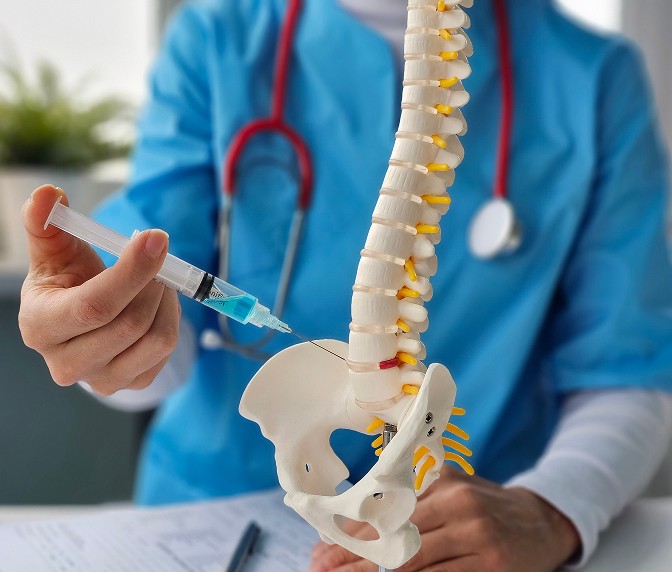
You may be a good candidate if you:
Treatment plans are individualized based on symptoms and functional goals.

Miami residents are highly active, and repetitive lifting, rotational sports, running, and gym-based training can place added stress on the spine. Treatment for active adults focuses on:
We aim to keep patients active while managing their condition safely.
Severe pain, persistent symptoms, weakness, numbness, or changes in bowel or bladder control warrant immediate medical attention.
Imaging studies like X-ray and MRI are ordered when it will meaningfully influence diagnosis or treatment planning. Imaging studies are not always necessary, and not always covered by insurance, when treating spine pain. Additionally, facet joint degenerative changes, or osteoarthritis, is often a normal finding on imaging studies.
Imaging studies like X-ray and MRI are ordered when it will meaningfully influence diagnosis or treatment planning. Imaging studies are not always necessary, and not always covered by insurance, when treating spine pain.
Recovery varies depending on the cause of pain, adherence to therapy, and overall health. Many patients experience improvement over several weeks to months.
A facet joint injection delivers medication directly inside the facet joint capsule. A medial branch block delivers local anesthetic along the small nerves supplying the facet joint — outside the joint itself. Both serve diagnostic and therapeutic purposes, but medial branch blocks are the standard first step in the pathway toward radiofrequency ablation. Dr. Bonner determines which approach is most appropriate based on your symptoms and the specific goals of the procedure.
For some patients, intraarticular BMAC offers an alternative to repeated RFA cycles by addressing the underlying facet joint degeneration rather than ablating the pain-transmitting nerves. Early clinical evidence is promising. Whether BMAC or RFA is the more appropriate approach depends on the severity of facet arthropathy, prior treatment response, and patient goals — and is discussed individually at consultation.
If you are experiencing facet join pain and want a comprehensive evaluation and non-surgical treatment plan, we are here to help. Contact our Miami clinic to schedule an appointment.
CONTACT US