
Degenerative disc disease (DDD) is one of the most common causes of chronic neck and low back pain — yet one of the most difficult to treat with conventional approaches. The intervertebral disc has limited vascularity and regenerative capacity, and steroid injections and pain medications do little to alter its degenerative trajectory. Intradiscal BMAC stem cell therapy is the most advanced non-surgical biological intervention currently available for discogenic pain — targeting the disc at the cellular level to support tissue repair in ways no other treatment can.
Dr. William Bonner, a credentialed Regenexx network provider in Miami, performs fluoroscopically-guided intradiscal BMAC injections for degenerative disc disease — a technically demanding procedure requiring specialized training not available at most pain management practices.
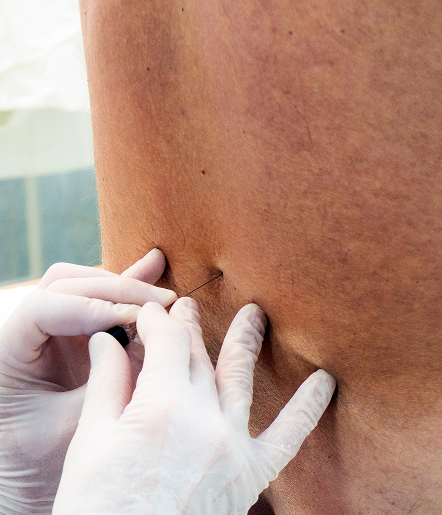
BMAC is injected directly into the nucleus pulposus under fluoroscopic guidance, acting on multiple targets simultaneously:
Patients often ask whether BMAC can be used for cervical disc degeneration as well as lumbar. The answer is yes, but with important distinctions:
Lumbar intradiscal BMAC is the more commonly performed application. The procedure is approached from a posterolateral direction under fluoroscopic guidance. The anatomy is generally more forgiving and the procedure is well-established within the Regenexx protocol framework.
Cervical intradiscal BMAC requires an anterior approach — the needle approaches the disc from the front of the neck, navigating carefully around the carotid artery, jugular vein, trachea, and esophagus. This is a more technically demanding procedure that requires specific expertise and is performed only in carefully selected patients with appropriate anatomy and clinical indication. Not every physician offering intradiscal BMAC for the lumbar spine performs the cervical procedure as well — it is a distinct technical skill.
Dr. Bonner evaluates cervical disc candidates individually and is transparent about the additional technical complexity and risks of the cervical approach during the consent process.
The evidence base for intradiscal biologics is at an earlier stage than the joint OA literature, but several important findings support the biological rationale and emerging clinical results.
Research on intradiscal PRP by Lutz et al. in PM&R provided early evidence that intradiscal injection of concentrated growth factors could produce meaningful pain reduction and functional improvement in patients with discogenic low back pain — establishing proof of concept for the biological approach to disc treatment. The same biological mechanisms apply to BMAC, with the addition of the mesenchymal stem cell component.
For BMAC specifically, published Regenexx registry data demonstrate meaningful improvements in pain and function following intradiscal BMAC in carefully selected patients with discogenic low back pain — with outcomes tracking confirming durability of response in a subset of appropriately selected patients.
The most important mechanistic evidence comes from disc biology research: mesenchymal stem cells delivered into the nucleus pulposus have been shown in laboratory and animal models to differentiate into nucleus pulposus-like cells, to stimulate proteoglycan synthesis by existing disc cells, and to suppress the pro-inflammatory cytokine environment that drives discogenic pain. The translation from bench to bedside is ongoing — but the biological foundation is strong.
Many clinics in Miami advertise ‘stem cell therapy’ using amniotic or umbilical cord products that independent research has shown to contain no viable living stem cells. As a credentialed Regenexx network provider, Dr. Bonner uses your own living bone marrow stem cells — harvested and processed the same day — under strict evidence-based protocols backed by the largest regenerative orthopedics outcome registry in the world. Regenexx is the only organization with this combination of proprietary lab processing, published clinical research, and rigorous provider credentialing.
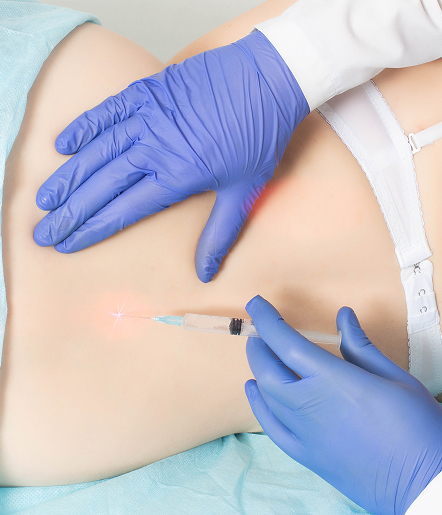
Bone marrow is aspirated from the posterior iliac crest under local anesthetic and ultrasound or fluoroscopic guidance, concentrated in-office using Regenexx protocols, then injected into the hip joint under fluoroscopic guidance with contrast confirmation. Full procedure time including processing is approximately 2.5 to 3.5 hours in a single visit.
Most patients resume light daily activities within 1–3 days. Improvement develops gradually over 6–12 weeks, with continued benefit over 3–6 months.
Complete reversal is not a realistic expectation. Intradiscal BMAC can support disc cell survival, suppress intra-discal inflammation, and potentially slow further degeneration — resulting in meaningful pain reduction and improved function for many patients.
No. Disc replacement and fusion are surgical procedures. Intradiscal BMAC is a minimally invasive injection that attempts to support the disc’s own biology — leaving the disc intact and avoiding surgical risks and recovery.
Many clinics use amniotic or cord products without living stem cells. Intradiscal BMAC uses your own living bone marrow cells, concentrated the same day, delivered under fluoroscopic guidance by a physician trained in this specific technique through the Regenexx network — a fundamentally different and more rigorous procedure.
Intradiscal healing is slower than peripheral joint healing. Most patients begin noticing improvement between 8 and 16 weeks, with continued improvement possible over 6–12 months.
Discogenic pain has characteristic features — typically deep, central or paracentral axial pain that worsens with prolonged sitting, forward flexion, and Valsalva maneuvers (coughing, sneezing). MRI findings consistent with disc degeneration (Pfirrmann grade III or higher, Modic endplate changes) that correlate anatomically with the symptom pattern support the diagnosis. In some cases, a diagnostic discogram — a procedure where contrast is injected into the disc to reproduce symptoms and confirm the pain source — provides additional confirmation. Dr. Bonner discusses the diagnostic workup in detail at your consultation.
Pfirrmann grade is an MRI classification system for disc degeneration, ranging from Grade I (normal, bright signal) to Grade V (complete collapse, no signal). For intradiscal BMAC, grades II through IV represent the therapeutic window where meaningful disc cell activity remains and the biological payload has something to work with. Grade V discs — completely collapsed with no remaining disc height — are generally not appropriate for intradiscal treatment because there is insufficient viable tissue to respond.
Yes. Intradiscal BMAC can be repeated in appropriately selected patients. If an initial procedure produces meaningful improvement that then fades over 1 to 2 years, a second treatment is a reasonable consideration. Dr. Bonner reviews the original imaging, the clinical response, and any updated imaging before recommending repeat treatment.
If you are dealing with chronic neck or low back pain, or degenerative spine conditions and want to explore whether BMAC therapy is right for you, we are here to help.
Contact our Miami clinic to schedule an appointment with Dr. Bonner, or book online through ZocDoc for available appointment times (if you do not see availability, please reach out to us directly at 786-522-4959).
BOOK ONLINE NOW